The main difference between Vyvanse and Ritalin is speed, because the body has to convert Vyvanse into its active form before the medicine starts working. Vyvanse starts slowly and lasts up to 14 hours, while immediate-release Ritalin starts in about 20 minutes and lasts about 4 hours.
Both medications are Schedule II controlled substances, the strictest category for drugs with an accepted medical use, and both treat attention-deficit/hyperactivity disorder (ADHD). Both carry an FDA Boxed Warning for abuse, misuse and addiction, and both cause physical dependence in some people who take them exactly as prescribed.
Stopping either drug suddenly after heavy use brings a crash of exhaustion, hunger and low mood that lasts several days, with some symptoms continuing for 1 to 2 weeks, according to SAMHSA. So which one works better for ADHD, which causes more side effects, and which carries more abuse risk for adults and teens?
What are Vyvanse and Ritalin?
Vyvanse and Ritalin are prescription central nervous system stimulants that raise dopamine and norepinephrine signaling in the brain, but they belong to different drug classes and reach the bloodstream through different routes.
What Vyvanse is and what it treats
Vyvanse is the brand name for lisdexamfetamine dimesylate, an amphetamine prodrug in which dextroamphetamine is covalently bonded to the amino acid l-lysine.
- The molecule arrives inactive: Lisdexamfetamine produces no stimulant effect until enzymes cleave the l-lysine and release dextroamphetamine.
- Absorption uses a peptide transporter: Peptide transporter 1 carries the intact molecule across the intestinal wall, after which hydrolysis occurs in the cytosol of red blood cells.
- Two indications carry Food and Drug Administration approval: Regulators approved Vyvanse for attention-deficit/hyperactivity disorder and for moderate to severe binge eating disorder in adults.
- Generic versions exist: Generic lisdexamfetamine entered the United States market after patent expiration, sold in capsule and chewable tablet forms.
What Ritalin is and what it treats
Ritalin is the brand name for immediate-release methylphenidate hydrochloride, a stimulant that is not an amphetamine and becomes pharmacologically active the moment it is absorbed.
- No conversion step exists: Methylphenidate blocks dopamine and norepinephrine transporters directly, without requiring metabolic activation.
- Immediate release drives short duration: Prescribers order two or three daily doses because the immediate-release formulation clears within several hours.
- Two indications carry approval: Regulators approved Ritalin for attention-deficit/hyperactivity disorder and for narcolepsy.
- Extended-release relatives exist separately: Extended-release methylphenidate formulations like Concerta deliver the same molecule across a longer window through a different delivery system.
What are the key differences between Vyvanse and Ritalin?
Vyvanse is a long-acting amphetamine prodrug taken once each morning that lasts up to 14 hours, while Ritalin is short-acting methylphenidate that starts in about 20 minutes, lasts about 4 hours and is taken 2 or 3 times a day. Both are Schedule II and both treat ADHD. Vyvanse also treats binge eating disorder in adults, and Ritalin also treats narcolepsy.
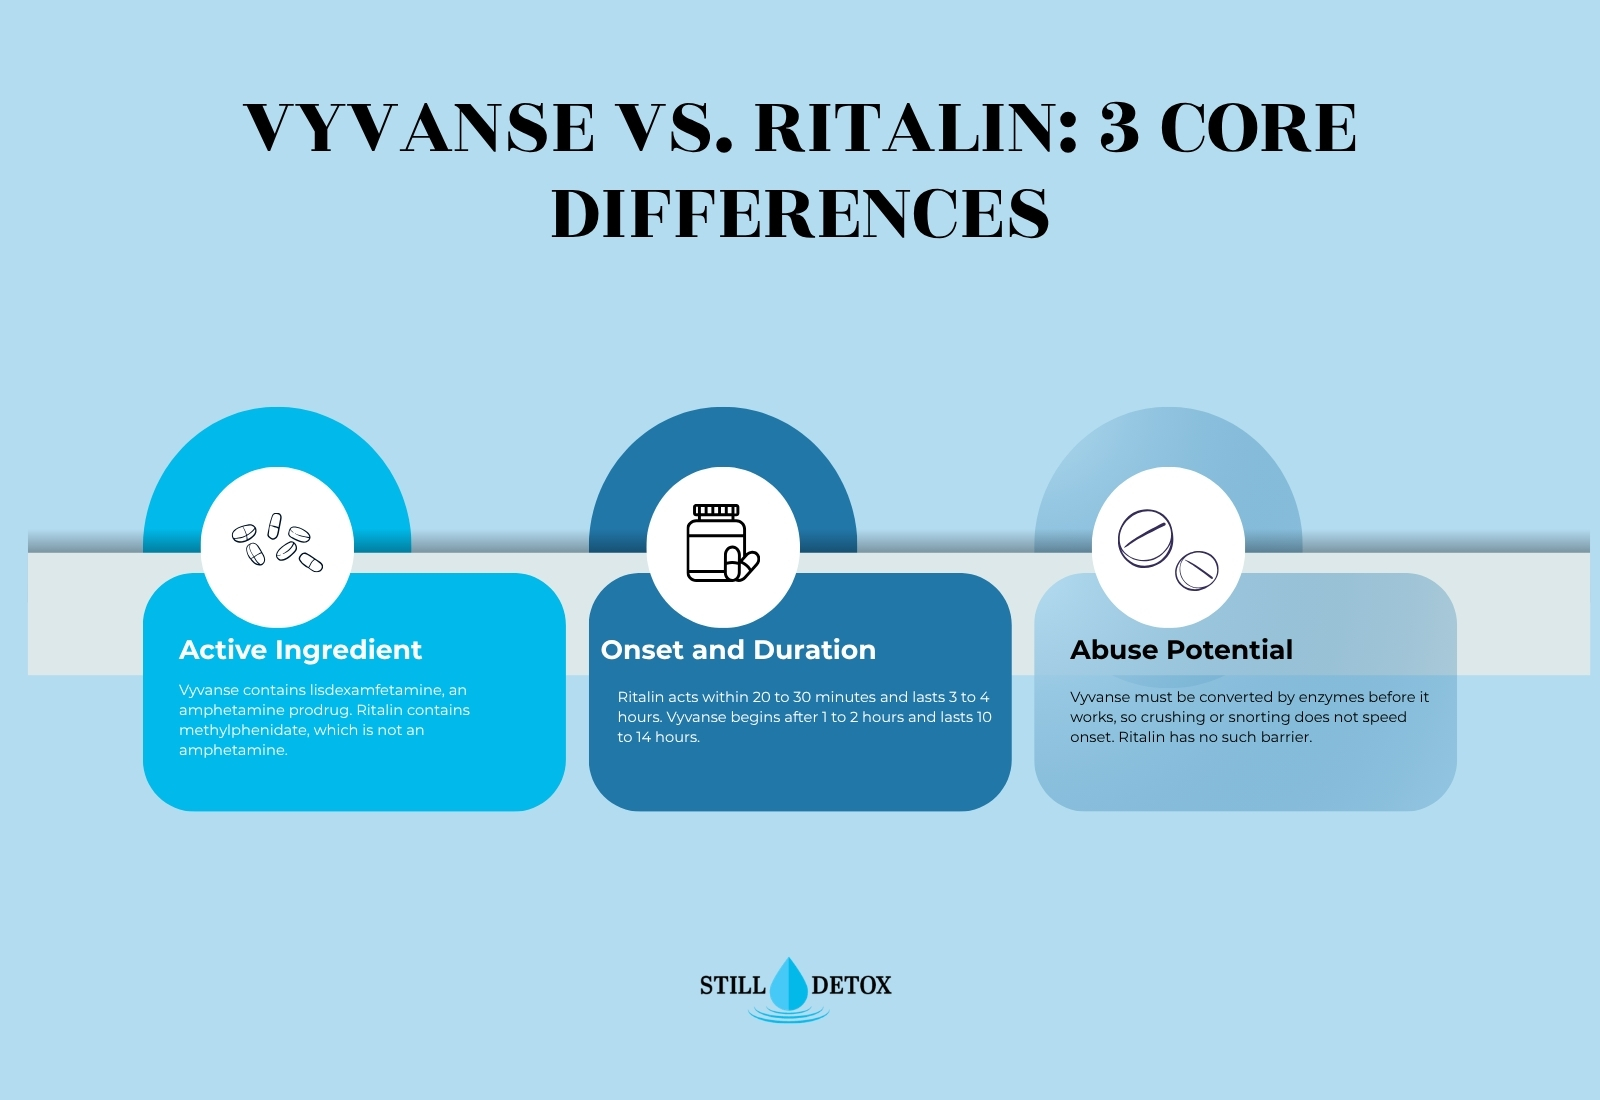
Side-by-side comparison of Vyvanse and Ritalin
The following comparison isolates the features that distinguish lisdexamfetamine from immediate-release methylphenidate.
| Feature | Vyvanse (lisdexamfetamine) | Ritalin (methylphenidate) |
|---|---|---|
| Drug class | Amphetamine prodrug | Methylphenidate, a non-amphetamine stimulant |
| Active compound | Dextroamphetamine, released after enzymatic hydrolysis | Methylphenidate, active on absorption |
| Release profile | Long-acting, single morning dose | Immediate release, two to three doses daily |
| Onset of effect | About 1.5 to 2 hours | About 20 minutes |
| Duration of effect | Up to 13 hours in children and 14 hours in adults | About 4 hours |
| DEA classification | Schedule II | Schedule II |
| Approved indications | ADHD, moderate to severe binge eating disorder | ADHD, narcolepsy |
| Effect of crushing or snorting | Injection does not skip the conversion step, but high doses are still misused; FDA Boxed Warning on snorting and injection | No conversion step to slow it; FDA Boxed Warning on snorting and injection |
How fast do Vyvanse and Ritalin work, and how long do they last?
Immediate-release Ritalin starts working in about 20 minutes, reaches its peak blood level at about 2 hours and lasts about 4 hours. Vyvanse starts working in about 1.5 to 2 hours, reaches its peak blood level at about 3.5 to 4 hours and lasts up to 14 hours in adults from a single morning dose. Ritalin is taken 2 or 3 times a day for that reason.
Vyvanse timeline after a single morning dose
Lisdexamfetamine produces a delayed and gradual rise because absorption must precede enzymatic conversion.
- Minutes 0 to 60: Peptide transporter 1 absorbs the intact prodrug, and no stimulant effect is present.
- Hours 1.5 to 2: Enzymes in red blood cells release dextroamphetamine, and FDA label studies first measured a benefit at 1.5 hours in children and 2 hours in adults.
- Hours 3.5 to 4: Dextroamphetamine reaches its peak blood level, at about 3.5 hours in children and 3.8 hours in fasting adults.
- Hours 4 to 12: Effect holds at a steady level without the sharp peaks of immediate-release stimulants.
- Hours 13 to 14: The FDA label studies measured benefit through 13 hours in children and 14 hours in adults, and how long lisdexamfetamine remains detectable extends beyond the period of noticeable effect.
Ritalin timeline after a single immediate-release dose
Immediate-release methylphenidate produces a rapid rise and an equally rapid decline, which is why prescribers divide the daily dose. Jaeschke and colleagues’ 2021 review in Psychopharmacology puts the onset at about 20 minutes, the peak blood level at 1 to 3 hours and the overall effect of Ritalin at about 4 hours.
- About 20 minutes: Methylphenidate begins occupying dopamine and norepinephrine transporters, and the effect starts.
- Hours 1 to 3: Blood levels peak, at an average of about 2 hours after a 10 mg tablet according to the FDA label, producing the strongest effect of the dosing interval.
- About hour 4: The effect wears off and symptom control weakens, prompting the next scheduled dose.
- Hours 4 to 6: Rebound symptoms including irritability, fatigue, and returning inattention appear in some patients as levels drop.
What forms and doses do Vyvanse and Ritalin come in?
Vyvanse comes as capsules from 10 to 70 mg and chewable tablets from 10 to 60 mg, usually started at 30 mg once each morning with a 70 mg daily maximum. Ritalin comes as 5, 10 and 20 mg tablets, taken 2 or 3 times a day, with a 60 mg daily maximum, according to the FDA labels. Only the prescriber sets or changes a dose.
The following table compares the forms and label doses of Vyvanse and immediate-release Ritalin.
| Feature | Vyvanse (lisdexamfetamine) | Ritalin (methylphenidate) |
|---|---|---|
| Forms | Capsules and chewable tablets | Tablets |
| Strengths | Capsules: 10, 20, 30, 40, 50, 60 and 70 mg. Chewable tablets: 10, 20, 30, 40, 50 and 60 mg | 5, 10 and 20 mg |
| Starting dose for ADHD | 30 mg every morning | Children 6 and older: 5 mg twice a day, before breakfast and lunch |
| Usual daily range for ADHD | 30 to 70 mg once a day | Adults: 20 to 30 mg a day, split into 2 or 3 doses |
| Maximum daily dose | 70 mg | 60 mg |
| How it is taken | In the morning; capsules can be swallowed whole or opened and mixed into yogurt, water or orange juice | 30 to 45 minutes before meals |
The Vyvanse label tells patients to avoid afternoon doses because of insomnia, and it lowers the maximum Vyvanse dose to 50 mg a day for people with severe kidney impairment. Extended-release forms of methylphenidate, such as Ritalin LA and Concerta, use different strengths and are dosed once a day.
Which works better for ADHD, Vyvanse or Ritalin?
Both Vyvanse and Ritalin reduce ADHD symptoms better than placebo, and neither is best for everyone. Cortese and colleagues’ 2018 review of 133 trials in The Lancet Psychiatry found amphetamines, the class that includes Vyvanse, reduced adult symptoms more, and recommended methylphenidate first for children and amphetamines first for adults.
The Cortese review weighed both symptom relief and how often people quit a trial because of side effects. There are 3 findings from that review that matter for the Vyvanse vs Ritalin choice:
- Adults: Clinician ratings showed a larger symptom improvement for amphetamines than for methylphenidate over about 12 weeks.
- Children and adolescents: Both classes beat placebo, and amphetamines were less well tolerated than placebo, which is why the authors placed methylphenidate first for this age group.
- Long-term data: The review found too little data at 26 and 52 weeks to compare the drugs over longer periods.
The FDA label for Vyvanse reports benefit in adults from 2 hours to 14 hours after a morning dose in a simulated workplace study. A prescriber chooses between Vyvanse and Ritalin based on age, how long symptom control needs to last each day, side effects, heart health and any history of substance use.
How do Vyvanse and Ritalin work in the brain?
Vyvanse and Ritalin both raise dopamine and norepinephrine concentrations in the prefrontal cortex, but methylphenidate blocks reuptake while amphetamine additionally forces neurotransmitter release.
How methylphenidate acts on dopamine transporters
Methylphenidate raises synaptic dopamine by occupying the dopamine transporter and preventing reabsorption of dopamine already released.
- Transporter blockade is the primary mechanism: Methylphenidate binds the dopamine transporter and the norepinephrine transporter, leaving both neurotransmitters in the synapse longer.
- Volkow measured the transporter blockade: Nora Volkow, now Director of the National Institute on Drug Abuse, and colleagues at Brookhaven National Laboratory used brain imaging (positron emission tomography) in 1998 to show that oral methylphenidate blocks the dopamine transporter, the same target cocaine acts on, and that typical treatment doses block more than 50 percent of these transporters, published in the American Journal of Psychiatry.
- The prefrontal cortex mediates the therapeutic effect: Increased norepinephrine and dopamine signaling in the prefrontal cortex improves sustained attention and impulse control.
- Rate of rise determines the subjective effect: Volkow and Swanson demonstrated in 2003 that how quickly dopamine rises, rather than how high it climbs, generates the reinforcing effect that drives misuse. This mechanism also explains why stimulants calm ADHD symptoms rather than causing agitation at therapeutic doses.
How amphetamine prodrugs act differently
Dextroamphetamine released from lisdexamfetamine blocks reuptake and additionally drives dopamine out of storage vesicles, producing a broader mechanism than methylphenidate.
- Vesicular release adds a second pathway: Amphetamine enters the neuron and disrupts vesicular monoamine transporter 2, pushing stored dopamine into the cytoplasm.
- Reverse transport follows: The dopamine transporter then runs backward, releasing dopamine into the synapse independently of neuronal firing.
- Trace amine-associated receptor 1 modulates the response: Amphetamine activates trace amine-associated receptor 1, which alters dopamine transporter function and amplifies the effect.
- Conversion imposes a rate limit: Because red blood cell hydrolysis releases dextroamphetamine gradually, the dopamine rise in the nucleus accumbens stays slower than with an equivalent immediate-release amphetamine such as mixed amphetamine salts.
What are the side effects of Vyvanse and Ritalin?
Vyvanse and Ritalin share a side effect profile driven by sympathetic nervous system activation, ranging from appetite suppression to cardiovascular and psychiatric emergencies.
Common side effects of Vyvanse and Ritalin
Common side effects of both stimulants appear within the first weeks of treatment and reflect elevated norepinephrine activity.
- Appetite suppression is near-universal: Both medications reduce hunger, and Vyvanse produces longer appetite suppression because its effect lasts up to 14 hours.
- Insomnia follows late dosing: Both stimulants delay sleep onset, particularly when a dose is taken in the afternoon or evening.
- Dry mouth and headache are frequent: Reduced salivary flow and tension headache accompany sympathetic activation.
- Heart rate and blood pressure rise modestly: Both medications elevate resting heart rate and blood pressure, which requires monitoring in patients with cardiovascular history.
- Irritability emerges as levels fall: The wearing-off period produces mood irritability, more noticeably with immediate-release Ritalin than with Vyvanse.
- Weight loss follows sustained appetite reduction: Continued appetite suppression produces weight loss, monitored closely in children and adolescents.
Severe side effects and effects when misused
Severe stimulant side effects concentrate in the cardiovascular and psychiatric systems and appear disproportionately when doses exceed what a prescriber ordered.
- Chest pain, shortness of breath, or fainting: These findings demand immediate emergency evaluation, because stimulants raise the risk of arrhythmia and, rarely, sudden cardiac events.
- Psychosis with hallucinations or paranoia: High doses precipitate stimulant-induced psychosis, which can occur even in people with no psychiatric history.
- Seizure activity: Stimulants lower the seizure threshold, and seizures at any dose require emergency assessment.
- Peripheral vasculopathy including Raynaud phenomenon: Both drugs constrict peripheral blood vessels, producing numbness, coolness, and color change in fingers and toes.
- Priapism: The Food and Drug Administration warns that methylphenidate products can cause prolonged, painful erections requiring urgent medical care.
- Severe agitation with high body temperature: This combination signals stimulant toxicity and requires emergency treatment.
- Suicidal thinking during withdrawal: Abrupt cessation after heavy use produces depressed mood severe enough to generate suicidal thoughts.
Long-term risks of prescription stimulant misuse
Long-term prescription stimulant misuse produces cumulative cardiovascular, psychiatric, and functional damage that persists beyond the period of active use.
- Sustained hypertension damages the cardiovascular system: Chronic blood pressure elevation raises long-term risk of stroke and cardiomyopathy.
- Repeated psychosis episodes raise recurrence risk: Each stimulant-induced psychotic episode increases the likelihood of subsequent episodes at lower doses.
- Nasal and sinus damage follows insufflation: Crushing and snorting methylphenidate tablets erodes nasal tissue and introduces tablet fillers not intended for mucosal contact.
- Malnutrition compounds over months: Prolonged appetite suppression produces measurable weight loss and micronutrient deficiency, a pattern also documented in heavy amphetamine use.
- Occupational and academic function declines: The performance improvement that motivated misuse reverses as tolerance, sleep loss, and withdrawal cycles accumulate.
What drugs should not be taken with Vyvanse or Ritalin?
Neither Vyvanse nor Ritalin can be taken with a monoamine oxidase inhibitor (MAOI), an older type of antidepressant, or within 14 days of stopping one, because the combination can cause a dangerous spike in blood pressure called a hypertensive crisis. Both labels also list an allergy to the drug as a reason not to use it.
The following are the interactions named in the FDA labels for each drug.
Vyvanse drug interactions
- MAOIs: Vyvanse is contraindicated with MAOIs, including linezolid and intravenous methylene blue, or within 14 days of stopping them.
- Serotonin-raising drugs: SSRIs, SNRIs, triptans, tricyclic antidepressants, fentanyl, lithium, tramadol, buspirone and St. John’s Wort raise the risk of serotonin syndrome, a dangerous reaction marked by agitation, fast heart rate, fever and muscle twitching.
- Urine pH changers: Alkalinizing agents raise amphetamine blood levels and should be avoided, while acidifying agents lower them.
- Tricyclic antidepressants: Tricyclic antidepressants can sharply raise brain levels of dextroamphetamine and strengthen heart effects.
Ritalin drug interactions
- MAOIs: Ritalin is contraindicated with MAOIs or within 14 days of stopping one, because of the risk of hypertensive crisis, stroke and heart attack.
- Blood pressure medicines: Ritalin lowers the effect of drugs used to treat high blood pressure, so the prescriber monitors blood pressure.
- Anesthesia: Halogenated anesthetics given with Ritalin raise the risk of sudden blood pressure and heart rate spikes during surgery, so Ritalin is avoided on the day of surgery.
- Risperidone: Changing the dose of risperidone or Ritalin while taking both raises the risk of movement side effects.
Both labels tell prescribers to check for heart disease before starting either drug and to avoid them in people with serious heart problems. A full medication list, including supplements, belongs in every conversation with the prescriber.
Which has a higher abuse risk, Vyvanse or Ritalin?
Both carry a high abuse risk under the FDA Boxed Warning, and the answer depends on how risk is measured. Immediate-release Ritalin reaches the brain faster, which makes each dose more reinforcing. Yet Han and colleagues found in 2025 that adults using amphetamine-type stimulants, the group that includes Vyvanse, were 3.1 times as likely to report misuse as adults using methylphenidate.
What does the FDA boxed warning say about Vyvanse and Ritalin?
The FDA Boxed Warning on Vyvanse and Ritalin states that each drug has a high potential for abuse and misuse that can lead to a substance use disorder, including addiction. On May 11, 2023, the FDA required this updated Boxed Warning, its most prominent warning, on every prescription stimulant.
The following are the 4 points the 2023 stimulant Boxed Warning and FDA safety update make:
- Overdose and death: Misuse and abuse of stimulants, including Vyvanse and Ritalin, can result in overdose and death.
- Higher doses and other routes: The risk rises with higher doses or with snorting or injection.
- Ongoing screening: Prescribers assess each patient’s risk of abuse, misuse and addiction before treatment and throughout it.
- No sharing: Patients are told never to share a stimulant, because the FDA states that most people who misuse prescription stimulants get them from family members or peers.
Why the Vyvanse prodrug design lowers abuse liability
The lisdexamfetamine prodrug structure lowers abuse liability at usual doses because the body must convert Vyvanse in red blood cells before it works, but the FDA label shows that high doses can still be misused.
- Injecting does not skip conversion: Injecting lisdexamfetamine does not skip the red blood cell step that releases dextroamphetamine, but high doses of Vyvanse are still misused, and the FDA Boxed Warning states that snorting or injecting raises the risk of overdose and death. In the FDA label, injected lisdexamfetamine produced more drug liking than placebo but less than injected dextroamphetamine.
- The dopamine rise stays gradual: Slower release produces a slower rise in nucleus accumbens dopamine, which reduces the euphoric reinforcement Volkow and Swanson identified as the driver of misuse.
- High doses erase the advantage: In an abuse study of 38 people with a history of drug misuse described in the FDA label, 100 mg of Vyvanse produced less drug liking than 40 mg of immediate-release dextroamphetamine, but 150 mg of Vyvanse produced similar drug liking.
- Lower liability is not zero liability: Vyvanse remains a Schedule II controlled substance, and taking doses above what a prescriber ordered still produces dependence.
Why immediate-release Ritalin carries a fast-onset misuse risk
Immediate-release methylphenidate carries a fast-onset misuse risk because its quick start and short duration create both a sharp reinforcing signal and frequent dosing opportunities.
- Onset in about 20 minutes produces a steep rise: Fast transporter occupancy generates the rapid dopamine increase that drives reinforcement.
- Snorting raises the danger further: Crushing and snorting Ritalin tablets removes even the short delay of swallowing, and the FDA Boxed Warning states that snorting or injecting raises the risk of overdose and death.
- Short duration multiplies dosing decisions: Three daily doses create three daily opportunities to take more than prescribed.
- Multiple daily doses complicate diversion tracking: Divided dosing makes missing tablets harder for prescribers and families to detect.
How diversion happens with both medications
Diversion of both stimulants occurs primarily through social networks rather than illicit markets, which shapes who develops stimulant use disorder.
- Sharing among peers is the dominant route: The FDA states that most people who misuse prescription stimulants get them from family members or peers.
- Misuse often starts with a real prescription: Han and colleagues found in 2025 that 72.9 percent of adults with prescription stimulant use disorder used only their own prescribed stimulants, so misuse frequently begins inside legitimate treatment.
- Counterfeit tablets add overdose risk: Pills purchased outside a pharmacy and sold as Adderall or Ritalin can contain methamphetamine or fentanyl, according to the DEA.
- Early warning signs precede disorder: Recognizing signs of prescription drug misuse allows intervention before dependence establishes itself.
Why do prescription stimulants cause dependence?
Prescription stimulant dependence develops when repeated dopamine surges in the nucleus accumbens downregulate receptor sensitivity, driving escalating doses to reproduce the original effect.
Neurobiological drivers of stimulant dependence
The neurobiology of stimulant dependence centers on the brain’s reward pathway adapting to repeated artificial dopamine elevation.
- Receptor downregulation produces tolerance: Sustained dopamine elevation reduces dopamine D2 receptor availability, which flattens the response to the same dose.
- Escalating doses follow tolerance: Reduced receptor sensitivity drives people to take more than prescribed to restore the earlier level of focus or energy.
- Route of administration accelerates the process: Insufflation and injection compress the time to peak concentration, which sharpens the reinforcing signal.
- Baseline dopamine falls during abstinence: Withdrawal produces a dopamine deficit state that generates fatigue, low mood, and craving.
Behavioral and situational drivers
Behavioral patterns convert a legitimate prescription into misuse, most often through performance demands rather than recreational intent.
- Academic and workplace pressure drives dose escalation: Students and professionals take extra doses to extend working hours, which establishes a pattern of using the medication outside its prescribed purpose.
- Untreated symptoms invite self-adjustment: Inadequate symptom control prompts people to change their own dose rather than return to the prescriber.
- Weight control becomes a secondary motive: Appetite suppression leads some people to continue or increase stimulants for reasons unrelated to attention.
- Availability normalizes sharing: Widespread prescribing makes stimulants accessible through friends and classmates, which is how most nonmedical use begins.
Comorbid conditions that raise dependence risk
Several co-occurring conditions raise prescription stimulant dependence risk through identifiable mechanisms.
- Untreated depression drives stimulant self-medication: Stimulants temporarily lift mood and energy, which reinforces use in people whose depressive symptoms remain untreated.
- Anxiety disorders complicate dosing: Stimulants worsen anxiety in some patients, who then add sedatives or alcohol, establishing a polysubstance pattern.
- Existing substance use disorder predicts stimulant misuse: A history of alcohol or cannabis use disorder raises the likelihood of misusing a prescribed stimulant, which is why dependence on prescription stimulants often appears alongside other substance use.
- Eating disorders interact with appetite suppression: Stimulant-induced appetite loss reinforces restrictive eating patterns and complicates both conditions.
How is stimulant use disorder diagnosed?
Clinicians diagnose stimulant use disorder using DSM-5-TR criteria, evaluating a pattern of stimulant use that produces clinically significant impairment across a 12-month period.
DSM-5-TR criteria for stimulant use disorder
The DSM-5-TR defines stimulant use disorder through 11 criteria, with severity graded by how many criteria a person meets within 12 months.
- Severity is graded by criteria count: Two to three criteria indicate mild stimulant use disorder, four to five indicate moderate, and six or more indicate severe.
- Loss of control appears across several criteria: Taking larger amounts than intended, unsuccessful attempts to cut down, and persistent craving reflect impaired control.
- Tolerance and withdrawal are excluded when medication is taken as prescribed: The DSM-5-TR does not count tolerance or withdrawal toward diagnosis in people taking stimulants under appropriate medical supervision.
- Functional consequences carry diagnostic weight: Failure to meet obligations at work or school, continued use despite interpersonal problems, and abandoning activities all count toward the diagnosis.
Screening with the Drug Abuse Screening Test
The Drug Abuse Screening Test provides a brief self-report screen that quantifies the severity of drug-related problems before formal assessment.
- The 10-item version is standard: The Drug Abuse Screening Test, 10-item version (DAST-10), asks about the past 12 months and yields a score from 0 to 10.
- Score bands map to severity: A score of 0 indicates no reported problems, 1 to 2 indicates low level, 3 to 5 moderate, 6 to 8 substantial, and 9 to 10 severe drug-related problems.
- The Adult ADHD Self-Report Scale addresses the other side of the question: The Adult ADHD Self-Report Scale, version 1.1 (ASRS-v1.1), screens for adult ADHD, where four or more marked items in Part A indicate symptoms consistent with the condition and warrant evaluation.
- Screening never replaces assessment: Both instruments identify who needs a clinical evaluation rather than establishing a diagnosis.
Signs a prescription has become a problem
Specific behavioral patterns distinguish appropriate stimulant use from misuse that warrants clinical attention.
- Running out of medication before the refill date: Early depletion indicates doses are being taken more frequently or at higher amounts than prescribed.
- Taking a dose to function rather than to focus: Needing the medication to get out of bed or to feel normal signals dependence rather than symptom management.
- Seeking prescriptions from multiple prescribers: Obtaining overlapping prescriptions is a defining pattern of stimulant use disorder.
- Changing the route of administration: Crushing, snorting, or injecting a medication intended for oral use marks a clear transition into misuse.
- Combining stimulants with alcohol or sedatives: Layering substances to manage stimulant side effects establishes a polysubstance pattern that raises overdose risk.
How is prescription stimulant addiction treated?
Treatment for prescription stimulant addiction relies primarily on behavioral therapy, because no medication holds Food and Drug Administration approval for stimulant use disorder.
First-line behavioral therapies
Behavioral therapies carry the strongest evidence base for stimulant use disorder and form the foundation of treatment.
- Contingency management holds the strongest evidence: This approach delivers structured incentives for verified abstinence and outperforms other single interventions for stimulant use disorder.
- Cognitive behavioral therapy restructures use patterns: Cognitive behavioral therapy identifies the performance demands and emotional states that precede stimulant use and builds alternative responses.
- The Matrix Model integrates multiple components: This structured 16-week outpatient protocol combines cognitive behavioral elements, family education, and drug testing specifically for stimulant users.
- Community reinforcement approach restructures reward: This modality builds non-drug sources of reinforcement in work, family, and social domains.
Medications for stimulant use disorder
No medication carries approval for stimulant use disorder, so prescribers target specific withdrawal symptoms rather than the disorder itself.
- No approved pharmacotherapy exists: The Food and Drug Administration has approved no medication for stimulant use disorder, unlike opioid or alcohol use disorder.
- Antidepressants address the crash-phase mood drop: Prescribers use bupropion or mirtazapine off-label when depressed mood persists past the acute withdrawal window.
- Trazodone and mirtazapine support sleep: Sleep restoration during withdrawal reduces relapse risk in the first weeks.
- Bupropion with injectable naltrexone is the strongest studied option: The ADAPT-2 trial, a completed phase 3 trial published by Trivedi and colleagues in the New England Journal of Medicine in 2021, found a response in 13.6 percent of adults with methamphetamine use disorder on the combination and 2.5 percent on placebo. The combination holds no approved indication for stimulant use disorder.
How does Still Detox treat prescription stimulant misuse?
Still Detox treats stimulant use disorder in Boca Raton, Florida, through residential treatment of up to 30 days, with integrated dual diagnosis care for co-occurring mental health conditions. People who misuse Vyvanse, Ritalin or other prescription stimulants usually admit directly to residential care, because stimulants do not require a medical taper.
Admission for stimulant misuse
Still Detox admits most people with stimulant use disorder directly to residential care, and uses medical detox when alcohol, benzodiazepines or opioids are also involved, because those substances need a medically supervised taper.
- Stimulants do not need a medical taper: Stimulant withdrawal does not carry the seizure risk of alcohol or benzodiazepine withdrawal, but low mood and suicidal thinking during the crash make close clinical support important.
- Medical oversight is physician-directed: Medical Director Dr. Gladys Martinez, DO, evaluates each new client in person within 24 hours, and nursing care is directed by Britney Marshall, RN, with 24/7 nursing coverage.
- Accreditation reflects independent review: Still Detox holds Joint Commission accreditation and licensure through the Florida Department of Children and Families.
- Polysubstance patterns are assessed on admission: Many people who misuse stimulants also use alcohol or sedatives, and that use decides whether care starts in medical detox.
Residential treatment of up to 30 days
Residential treatment of up to 30 days at Still Detox delivers the behavioral therapy that forms the primary evidence-based treatment for stimulant use disorder.
- Cognitive and dialectical behavior therapies anchor the program: Still Detox delivers cognitive behavioral therapy and dialectical behavior therapy as core clinical modalities, with daily group therapy and individual therapy.
- Daily programming covers the first weeks after stopping: Residential care in Boca Raton includes 5.5 to 6 hours of clinical programming each day, during the weeks when mood and sleep are recovering after stimulant use stops.
- Twelve-step resources are available: Daily 12-step resources are offered as a voluntary part of the program, alongside individual and group therapy.
- Transgender clients are planned for individually: Still Detox in Boca Raton is a co-ed facility that plans care for transgender clients individually.
Dual diagnosis care for ADHD and co-occurring conditions
Co-occurring mental health conditions receive concurrent treatment at Still Detox, which matters because untreated ADHD, depression, or anxiety predicts return to stimulant misuse.
- Genuine ADHD requires a forward plan: Patients with confirmed ADHD need a management strategy developed with a prescriber, because leaving the condition untreated raises relapse risk.
- Depression and anxiety are assessed after the crash resolves: Acute withdrawal mimics depression, so psychiatric assessment carries more accuracy once the crash phase has passed.
- Misuse of prescribed medications is addressed directly: Still Detox treats misuse of prescribed medications alongside other substance use disorders.
What else do people ask about Vyvanse and Ritalin?
Is Ritalin stronger than Vyvanse?
No, neither medication is uniformly stronger. Ritalin produces a faster and sharper rise in dopamine because methylphenidate needs no conversion, so its effect feels more abrupt. Vyvanse delivers a steadier effect for up to 14 hours because red blood cell enzymes release dextroamphetamine gradually. Comparing milligram amounts between the two is meaningless, since they act through different mechanisms.
Why do people switch from Ritalin to Vyvanse?
Prescribers often move patients to Vyvanse when immediate-release methylphenidate wears off mid-afternoon and produces rebound irritability. A single Vyvanse dose covers a full day without repeat dosing. Clinicians also select Vyvanse when misuse is a concern, because the body releases its active drug slowly, though high doses of Vyvanse can still be misused. That decision belongs to a prescribing physician.
Is Ritalin addictive?
Yes. Ritalin carries an FDA Boxed Warning for abuse, misuse and addiction, and the Drug Enforcement Administration lists methylphenidate in Schedule II. At treatment doses, oral methylphenidate blocks more than half of the brain’s dopamine transporters, the same target cocaine acts on. Snorting Ritalin or taking more than prescribed raises the risk of addiction and overdose.
How long does Ritalin last compared to Vyvanse?
Immediate-release Ritalin starts working in about 20 minutes and lasts about 4 hours, which is why prescribers order 2 or 3 doses a day. Vyvanse starts working in about 1.5 to 2 hours and lasts up to 14 hours in adults on a single morning dose. The required conversion step explains both the delayed onset and the longer duration.
Can you become dependent on Vyvanse if you take it as prescribed?
Yes. Physical dependence develops in some people taking Vyvanse exactly as prescribed, producing fatigue and low mood if the medication stops abruptly. Dependence differs from addiction. Addiction involves compulsive use and loss of control, which the DSM-5-TR classifies as stimulant use disorder. Anyone stopping long-term stimulant therapy should do so under physician supervision.
What happens if you stop taking Vyvanse or Ritalin suddenly?
Abrupt discontinuation triggers a withdrawal crash marked by extreme fatigue, increased appetite, vivid dreams, and depressed mood. The crash lasts several days, and some symptoms continue for 1 to 2 weeks, according to SAMHSA. Suicidal thinking emerges in some people during this window, which makes medical supervision important for anyone stopping after heavy or prolonged use.
Which stimulant causes more weight loss?
Both suppress appetite, but amphetamine-based Vyvanse generally produces stronger and longer-lasting appetite reduction because its effect lasts up to 14 hours. Shorter-acting Ritalin allows appetite to return between doses. The Food and Drug Administration approved Vyvanse for moderate to severe binge eating disorder, though weight loss is not an approved use for either medication.
Can adults take Ritalin and Vyvanse together?
Sometimes, under a physician’s care. Prescribers occasionally combine a long-acting stimulant with a short-acting one to extend afternoon coverage, but that decision requires a physician and cardiovascular monitoring. Combining amphetamine and methylphenidate compounds blood pressure elevation, heart rate increase, and insomnia risk. Taking both without a prescription substantially raises the chance of stimulant-induced psychosis and cardiovascular emergency.
Sources
- Volkow, N. D., Wang, G.-J., Fowler, J. S., Gatley, S. J., Logan, J., Ding, Y.-S., Hitzemann, R., & Pappas, N. (1998). Dopamine transporter occupancies in the human brain induced by therapeutic doses of oral methylphenidate. American Journal of Psychiatry, 155(10), 1325-1331.
- Volkow, N. D., & Swanson, J. M. (2003). Variables that affect the clinical use and abuse of methylphenidate in the treatment of ADHD. American Journal of Psychiatry, 160(11), 1909-1918.
- Sharman, J., & Pennick, M. (2014). Lisdexamfetamine prodrug activation by peptidase-mediated hydrolysis in the cytosol of red blood cells. Neuropsychiatric Disease and Treatment, 10, 2275-2280. https://doi.org/10.2147/NDT.S70382
- Substance Abuse and Mental Health Services Administration. (2024). Key substance use and mental health indicators in the United States: Results from the 2023 National Survey on Drug Use and Health. https://www.samhsa.gov/data/
- Han, B., Jones, C. M., Volkow, N. D., Rikard, S. M., Dowell, D., Einstein, E. B., Guy, G. P., Tomoyasu, N., Ko, J., Baldwin, G., Olsen, Y., & Compton, W. M. (2025). Prescription stimulant use, misuse, and use disorder among US adults aged 18 to 64 years. JAMA Psychiatry, 82(6), 572-581. https://doi.org/10.1001/jamapsychiatry.2025.0054
- Takeda Pharmaceuticals America. (2026). Vyvanse (lisdexamfetamine dimesylate) capsules and chewable tablets, CII: Prescribing information. DailyMed, U.S. National Library of Medicine. https://dailymed.nlm.nih.gov
- Sandoz Inc. (2025). Ritalin (methylphenidate hydrochloride) tablets, CII: Prescribing information. DailyMed, U.S. National Library of Medicine. https://dailymed.nlm.nih.gov
- U.S. Food and Drug Administration. (2023, May 11). FDA updating warnings to improve safe use of prescription stimulants used to treat ADHD and other conditions. https://www.fda.gov
- Cortese, S., Adamo, N., Del Giovane, C., Mohr-Jensen, C., Hayes, A. J., Carucci, S., et al. (2018). Comparative efficacy and tolerability of medications for attention-deficit hyperactivity disorder in children, adolescents, and adults: A systematic review and network meta-analysis. The Lancet Psychiatry, 5(9), 727-738. https://doi.org/10.1016/S2215-0366(18)30269-4
- Jaeschke, R. R., Sujkowska, E., & Sowa-Kućma, M. (2021). Methylphenidate for attention-deficit/hyperactivity disorder in adults: A narrative review. Psychopharmacology, 238(10), 2667-2691. https://doi.org/10.1007/s00213-021-05946-0
- Trivedi, M. H., Walker, R., Ling, W., et al. (2021). Bupropion and naltrexone in methamphetamine use disorder. New England Journal of Medicine, 384(2), 140-153. https://doi.org/10.1056/NEJMoa2020214
- U.S. Drug Enforcement Administration. (n.d.). Fake prescription pills [Fact sheet]. https://www.dea.gov
- Substance Abuse and Mental Health Services Administration. (2021). Treatment for stimulant use disorders (Treatment Improvement Protocol [TIP] Series 33). https://www.ncbi.nlm.nih.gov/books/NBK576550/
- American Psychiatric Association. (2022). Diagnostic and statistical manual of mental disorders (5th ed., text rev.).